Diarrhoea overwhelms the gut; Acute Kidney Injury shuts down the filters. For a sick child, it’s not just fluid loss; it’s organ failure hiding in plain sight, masked by a symptom we think we understand.
When a child develops severe diarrhoea, a serious infection, or a critical illness, most parents worry about dehydration, fever, or breathing difficulties. Yet a potentially life-threatening complication can develop quietly in the background: acute kidney injury (AKI).
Once considered primarily an adult condition, AKI is now known to affect children of all ages, from newborns in neonatal units to teenagers in intensive care wards, and can lead to permanent kidney damage, chronic kidney disease, or death if not caught early.

Studies show AKI is common in hospitalised children, particularly in low- and middle-income countries where infections, dehydration and delayed access to healthcare remain widespread. A 2023 systematic review and meta-analysis of 94 studies involving more than 202,000 children from 26 countries found that about 26 per cent of hospitalised children develop some form of AKI, while about 14 per cent develop moderate to severe disease.
Mortality associated with AKI affects about 11 per cent of paediatric patients globally and is substantially higher in resource-limited settings. In Kenya, data from Kenyatta National Hospital (KNH) shows that nearly one in five children admitted to general paediatric wards develops the condition.
AKI is the abrupt loss of kidney function occurring over hours to days. Speaking during a webinar titled Saving Kidneys, Saving Lives: Paediatric AKI Management, Dr Shamsa Yahya, Consultant Paediatrician and Paediatric Nephrology Fellow at the University of Nairobi, describes it as a decline in the kidneys’ ability to filter blood effectively, leading to the retention of waste products such as urea and creatinine, while also disrupting fluid, electrolyte and acid-base balance.
When kidney function deteriorates, removal of waste products and regulating body fluids become compromised
Healthy kidneys remove waste products, regulate body fluids, maintain electrolyte balance, help control blood pressure, and produce hormones necessary for red blood cell production and bone health. When kidney function suddenly deteriorates, these vital processes become compromised.
Clinicians diagnose AKI using criteria developed by Kidney Disease: Improving Global Outcomes (KDIGO), based on a rapid rise in serum creatinine levels or a reduction in urine output.

A 2025 KNH study on children aged one month to 12 years admitted to general paediatric wards found an AKI prevalence of 19.9 per cent. Among affected children, 25.4 per cent required dialysis, while the mortality rate reached 23.4 per cent, compared to 9.6 per cent among children without AKI.
The burden appears even greater among newborns and critically ill children. Dr Yahya cites a KNH neonatal study involving 332 newborns, in which 120 infants were diagnosed with AKI, representing a prevalence of 36.1 per cent. Another study conducted among critically ill children found that 100 out of 117 patients had AKI, yielding a prevalence of 85.5 per cent. “These findings demonstrate why kidney function assessment is essential in critically ill children,” she notes. Risk factors associated with severe AKI included neonatal sepsis, maternal fever before delivery, younger age, female sex and gastroenteritis.
AKI arises from problems occurring before the kidneys (pre-renal), within the kidneys themselves (intrinsic or renal), or after the kidneys (post-renal).
Reduced kidney perfusion can occur because children lose excessive fluids through diarrhoea
Pre-renal AKI accounts for about 50 to 60 per cent of cases globally and in Kenya, and develops when blood flow to the kidneys is reduced. Common causes include severe diarrhoea and vomiting, dehydration, blood loss from trauma, severe infections and sepsis, burns, pneumonia and heart failure.
Dr Yahya explains that this form is often reversible if caught early. “Reduced kidney perfusion can occur because children lose excessive fluids through diarrhoea, vomiting or fever. If intervention happens promptly, kidney function can recover completely,” she says.
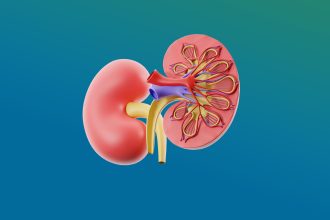
Intrinsic or renal AKI occurs when kidney tissue itself becomes damaged, whether through nephrotoxic medications such as certain antibiotics, ibuprofen and diclofenac, or conditions including glomerulonephritis, lupus nephritis, kidney infections, haemolytic uraemic syndrome, tumour lysis syndrome and sepsis-related inflammation. One of the most common mechanisms is acute tubular necrosis, which develops when pre-renal AKI is left untreated for too long and prolonged oxygen deprivation damages kidney cells.
Post-renal AKI accounts for about 5 to 10 per cent of cases and occurs when urine cannot drain normally due to an obstruction, such as congenital urinary tract abnormalities, posterior urethral valves, kidney stones or tumours. When the obstruction is removed early, kidney function can often recover.
Common warning signs include reduced urine output, swelling of the face, legs, hands or abdomen, fatigue, poor feeding, nausea and vomiting, high blood pressure, shortness of breath, irritability, confusion and seizures in severe cases.
A child may still pass urine and yet have significant kidney injury and thus lab testing is essential
Dr Yahya cautions, however, that AKI does not always present with reduced urine output. “A child may still pass urine and yet have significant kidney injury. That is why laboratory testing remains essential,” she says.
Diagnosis relies on blood urea levels, serum creatinine measurements, electrolyte testing, urinalysis, kidney and urinary tract ultrasound scans, full blood counts and infection screening. Urinalysis can provide valuable clues: concentrated urine may indicate dehydration-related AKI, while blood in urine may suggest glomerulonephritis. Blood pressure monitoring is equally important because hypertension frequently accompanies severe kidney injury.
Management focuses first on identifying and treating the underlying cause. “If the child has sepsis, we treat the infection. If the injury is caused by nephrotoxic drugs, those medications should be stopped. If there is an obstruction, it must be relieved,” Dr Yahya explains.
Fluid management is central to treatment, with clinicians monitoring every millilitre of fluid entering and leaving the child’s body, alongside daily weight measurements. Additional treatment may include rehydration therapy, antibiotics, correction of electrolyte abnormalities, blood pressure control, nutritional support and adjustment of medication doses. Nutrition plays a particularly important role because AKI places the body in a highly catabolic state, often requiring collaboration with nutrition specialists.
Children with severe kidney failure may require dialysis. Peritoneal dialysis, haemodialysis and continuous renal replacement therapy are available options, with peritoneal dialysis being the most practical. “It is relatively inexpensive, does not require vascular access, and can be performed even in low-resource settings,” Dr Yahya says. The method uses the lining of the abdomen as a natural filter, and typically does not cause alterations in the haemodynamic stability of a child.
Children who survive severe AKI face a higher risk of developing chronic kidney disease
Many cases of paediatric AKI are preventable. Key measures include prompt treatment of diarrhoea and dehydration, early management of infections and sepsis, improved maternal healthcare, avoidance of harmful herbal remedies, judicious use of nephrotoxic medications, malaria prevention through insecticide-treated nets, and early recognition of warning signs by caregivers and healthcare workers.

Recovery from AKI does not always mark the end of the story. Research increasingly shows lasting health effects: children who survive severe AKI face a higher risk of developing chronic kidney disease, persistent hypertension affects about 16 per cent of survivors, and proteinuria affects around 20 per cent. Follow-up care is therefore essential, with children typically reviewed two weeks after discharge, then at three months, six months, and annually thereafter.
In Kenya, where diarrhoeal diseases, infections and neonatal complications remain common, greater awareness among parents, caregivers and healthcare workers could prevent many children from progressing to severe kidney failure. Recognising the warning signs, seeking prompt medical attention and strengthening early diagnosis may be the difference between full recovery and lifelong kidney disease.